PAINFUL CLICKING AROUND THE SHOULDER BLADE: THE ROLE OF MRI IN DETECTING SCAPULOTHORACIC IMPINGEMENT
10/15/2026 10:10:51 AM
A 29-year-old male presented to the musculoskeletal clinic with a several-year history of persistent pain around the left shoulder blade, with no history of trauma. His characteristic symptoms occurred when moving his arm backward, producing a clicking sound around the scapula accompanied by pain and a grinding sensation during movement.
Scapular clicking can occur in otherwise healthy individuals. However, when the clicking is recurrent, painful, and clearly associated with a specific movement, a mechanical abnormality at the scapulothoracic interface should be considered. This is a deep, anatomically complex region that can be difficult to assess fully using conventional imaging modalities.
The patient was referred by an orthopedic specialist for an MRI of the left scapulothoracic region to identify the cause of pain and evaluate for associated abnormalities.
MRI FINDINGS OF THE LEFT SCAPULOTHORACIC REGION
Non-contrast MRI demonstrated the following findings:
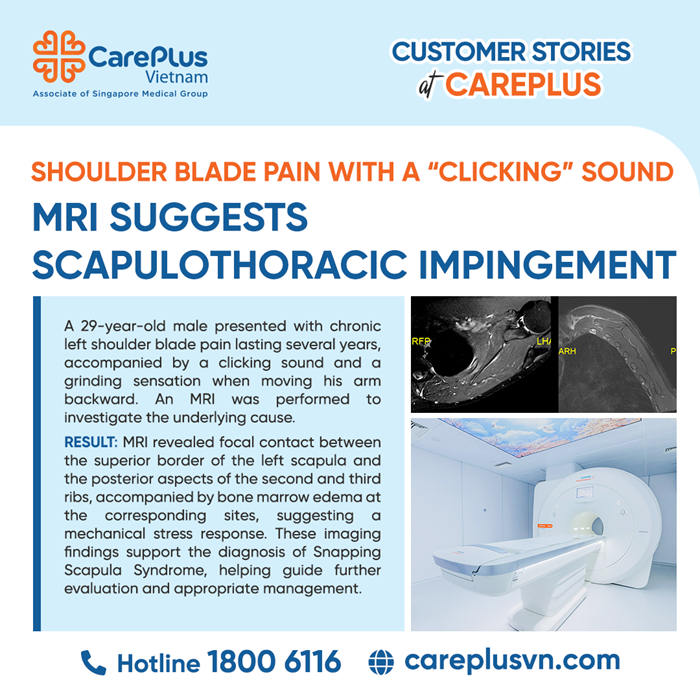
- Focal approximation between the superior border of the left scapula and the posterior aspects of the second and third ribs, resulting in relative narrowing of the scapulothoracic gliding space at this location.
- Prominent bone marrow edema in the posterior aspects of the second and third ribs, directly opposite the superior border of the scapula. The anatomical correspondence suggests a mechanical stress response associated with the abnormal contact.
- Mild focal edema in the adjacent muscle tissue near the area of contact. However, the periscapular muscles remained preserved in volume, with no evidence of muscle atrophy or fatty infiltration suggestive of chronic denervation.
- The superomedial angle of the scapula remained intact. No osteochondroma, acute fracture, or aggressive osseous lesion was identified.
- No significant fluid distension of the supraserratus or infraserratus bursae was observed. However, the absence of distended bursae does not completely exclude mechanical scapulothoracic impingement.
DIAGNOSTIC IMPRESSION
The combination of focal approximation between the superior scapular border and the posterior aspects of the second and third ribs, reactive bone marrow edema in the corresponding ribs, mild adjacent soft-tissue edema, and movement-related pain and clicking suggests mechanical scapulothoracic impingement.
In the context of painful clicking reproducible during physical examination, these MRI findings support the diagnosis of Snapping Scapula Syndrome.
This relatively uncommon clinical syndrome occurs when the normal gliding motion of the scapula over the chest wall is impeded by factors such as bony abnormalities, space-occupying lesions, bursitis, muscle pathology, or altered scapular kinematics.
THE VALUE OF MRI IN THIS CASE
MRI provides important information that may not be adequately demonstrated by conventional radiography:
- Detection of bone marrow response: Bone marrow edema does not necessarily indicate a fracture and is not entirely specific for impingement. However, when located precisely at the scapulothoracic contact site, it strongly suggests an active mechanical stress response.
- Assessment of deep soft tissues: MRI enables evaluation of the periscapular muscles, bursae, and soft tissues between the scapula and chest wall.
- Evaluation of the periscapular muscles: The absence of muscle atrophy or fatty infiltration makes advanced chronic denervation less likely. However, static MRI cannot exclude scapular dyskinesis or early neuromuscular abnormalities.
- Guidance for management: When no space-occupying lesion or destructive bone abnormality is identified, MRI findings may support an initial conservative approach, including activity modification, postural correction, and rehabilitation to restore periscapular muscle control.
IS MRI THE DEFINITIVE DIAGNOSTIC METHOD?
Snapping Scapula Syndrome is a dynamic condition, whereas MRI is performed in a static position. Therefore, MRI does not directly capture the snapping or friction of the scapula during movement. The final diagnosis must be based on the correlation between the patient's history, pain location, reproducible clicking, and dynamic assessment of scapular movement.
When detailed evaluation of bony anatomy or preoperative planning is required, three-dimensional CT reconstruction may provide additional information. Dynamic ultrasound and image-guided local anesthetic injection into a bursa may also be useful in selected cases.
Young patients experiencing persistent shoulder blade pain accompanied by clicking during movement should undergo assessment by an orthopedic or musculoskeletal specialist to establish an accurate diagnosis and determine disease severity.
In this case, MRI identified focal approximation between the superior scapular border and the posterior aspects of the second and third ribs, together with reactive bone marrow edema in the corresponding ribs. These findings provide valuable imaging evidence supporting mechanical scapulothoracic impingement and offer a plausible explanation for the patient's symptoms.
The key value of MRI lies not in independently establishing the syndrome, but in detecting subtle abnormalities, localizing the suspected site of impingement, and excluding important structural causes. When interpreted alongside clinical examination, MRI becomes an essential component of the diagnostic process for this uncommon but potentially overlooked condition.